



















Planning a visit? See Endometriosis care in South Plainfield for what care at our clinic involves.
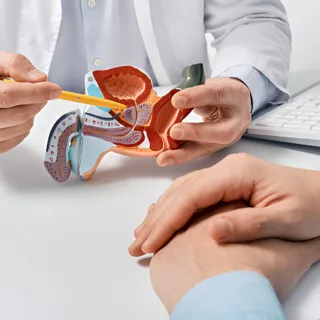
Some cramping with a period is common and usually harmless. Pain that keeps you home from work or school, that does not ease with over-the-counter pain relievers, or that shows up outside your period is not something to accept as normal, and endometriosis is one of the main conditions doctors look for. Endometriosis is tissue similar to the uterine lining growing outside the uterus. It cannot be confirmed by symptoms alone, there is no cure at present, and treatment aims to control pain and protect fertility.
Ordinary period pain versus pain with a cause
Doctors divide period pain (dysmenorrhea) into two types. Primary dysmenorrhea is caused by contractions of the uterus itself. It is the usual kind: the Office on Women's Health says more than half of women who have periods have some pain with them. Over-the-counter anti-inflammatory pain relievers ease it for most women.
Secondary dysmenorrhea is pain caused by another condition. Endometriosis, uterine fibroids, adenomyosis (uterine lining tissue within the muscle wall of the uterus) and scarring from pelvic infection are the usual suspects. Clues that point this way include pain at times other than just before or during a period, pain with sex or bowel movements, and pain that over-the-counter medicine does not relieve.
What endometriosis is and how common it is
In endometriosis, patches of tissue resembling the uterine lining grow on the ovaries, fallopian tubes, the outer surface of the uterus and the ligaments that hold it in place. These patches respond to monthly hormone changes, and they provoke inflammation and scarring.
The World Health Organization estimates that endometriosis affects about 10% of women of reproductive age, roughly 190 million worldwide. In the United States, the Office on Women's Health puts the figure at more than 11% of women aged 15 to 44, over 6.5 million women. The cause is not known. Backward flow of menstrual blood through the fallopian tubes is the leading theory, and genetics, the immune system and estrogen all appear to contribute. It is more likely if a close relative has it, if periods last more than seven days, or if cycles are 27 days or shorter.
Symptoms
- Very painful menstrual cramps that may worsen over the years
- Long-lasting pain in the lower back and pelvis
- Deep pain during or after sex
- Painful bowel movements or urination during periods
- Bleeding or spotting between periods
- Diarrhea, constipation, bloating or nausea, especially around periods
- Difficulty getting pregnant
The picture varies a great deal from one woman to the next. Some have no symptoms and learn of the condition only during a fertility work-up, while others live with pelvic pain most days of the month.
How it is diagnosed, and why it takes so long
The WHO reports that the average time from first symptoms to diagnosis is between 4 and 12 years. The symptoms overlap with other conditions, and confirming the diagnosis has traditionally required surgery.
A typical work-up includes:
- History and pelvic exam. A doctor may feel cysts or tender areas of scarring.
- Imaging. Ultrasound or MRI can show ovarian endometriosis cysts and some deeper disease. A normal scan does not rule endometriosis out.
- A trial of medicine. If pain improves on hormonal birth control or similar treatment, endometriosis becomes more likely.
- Laparoscopy. Keyhole surgery lets the surgeon see the patches and take a sample. The Office on Women's Health describes it as the only way to be certain.
Practice is shifting. The 2022 guideline from the European Society of Human Reproduction and Embryology questions whether laparoscopy with tissue sampling should still be treated as the required gold-standard test, which means more women are now treated on the basis of symptoms and imaging without surgery first.
Standard treatment
Pain relievers
Nonsteroidal anti-inflammatory drugs (NSAIDs) such as ibuprofen and naproxen are first-line for period pain. A Cochrane review of 80 randomized trials with 5,820 women with primary dysmenorrhea estimated that if 18% of women get moderate or excellent relief on placebo, between 45% and 53% will on an NSAID. Side effects, including stomach upset, were somewhat more frequent than with placebo. NSAIDs are not suitable for everyone, so check with your doctor or pharmacist if you have stomach, kidney or heart problems or take blood thinners.
Hormonal treatment
For women not trying to conceive, hormonal birth control is usually the next step. Pills taken continuously, injections and hormonal IUDs reduce or stop periods and with them much of the pain. Stronger options, including GnRH medicines that temporarily switch off ovarian hormone production, are used when these are not enough. Symptoms often return when hormonal treatment stops.
Surgery
Laparoscopic surgery to remove endometriosis patches is considered for severe symptoms, when hormones have not helped, or when fertility is affected. Hormonal treatment is often restarted afterward unless pregnancy is planned.
Fertility
Many women with endometriosis conceive without help, but it can be harder. The WHO notes that endometriosis is found in 25% to 50% of women with infertility. If you have been trying without success, ask for a referral.
The WHO states that no existing treatment definitively cures the disease. Pain often eases after menopause.
Acupuncture: what the evidence shows
For ordinary period pain
This is one of the most studied uses of acupuncture, and the results are less clear than the volume of research suggests. A 2016 Cochrane review included 42 randomized trials with 4,640 women. Acupuncture gave lower pain scores than no treatment and, in several trials, than NSAIDs. But comparisons with sham acupuncture were inconsistent, and the one sham-controlled trial at low risk of bias found no difference at 3, 6 or 12 months. Evidence quality was rated low or very low throughout. The reviewers concluded there was insufficient evidence to show whether acupuncture or acupressure works for primary dysmenorrhea.
A later exploratory trial found that menstrual pain fell in all acupuncture groups over three months and stayed lower for up to a year, but it had no untreated or sham comparison group, so it cannot separate the effect of needling from expectation and time.
For endometriosis pain
The evidence base is smaller. A 2011 Cochrane review found only one eligible trial, with 67 participants. A 2017 meta-analysis pooled 10 studies with 589 patients and found pain fell about 1.4 points more on a 10-point scale with acupuncture than with comparison treatments. Only one of those ten studies used a placebo control, and all were small.
The best trial so far was published in 2023. Researchers at four hospitals in China randomized 106 women with endometriosis pain to real or sham acupuncture for 12 weeks, with sessions three times a week starting a week before each expected period. Period pain fell more with real acupuncture, pain lasted for less time, and quality-of-life scores improved more. Two caveats matter. The advantage over sham had disappeared 12 weeks after treatment ended. And pelvic pain outside of periods and pain with sex improved no more with real acupuncture than with sham. No serious side effects were recorded.
What this means in plain terms: acupuncture may reduce period pain from endometriosis while treatment continues. It has not been shown to shrink endometriosis, improve fertility or replace hormonal treatment or surgery. Trial schedules were intensive, which is worth weighing against cost and time. Our article on how many acupuncture sessions are typically needed covers frequency in general terms.
Herbs, diet and Ayurveda
Chinese herbal medicine. A Cochrane review found just two randomized trials with 158 women. Herbal treatment after surgery performed about as well as a hormonal drug in one, and better than another drug for period pain in the second. Neither trial used a placebo, and the reviewers called for more rigorous research.
Ginger. For primary period pain (not endometriosis), a meta-analysis of four placebo-controlled trials found suggestive evidence that 750 to 2,000 mg of ginger powder during the first three to four days of the cycle reduces pain. The trials were small. Check with your doctor or pharmacist before using ginger supplements, especially if you take blood thinners, and ask your obstetric provider first if you are or could be pregnant.
Diet. A systematic review of dietary changes for endometriosis found nine human studies, each testing a different intervention. Most reported benefit, but the studies carried a moderate or high risk of bias. There is no proven "endometriosis diet."
Ayurveda. Ayurvedic treatment for endometriosis has not been tested in adequate clinical trials. Federal health authorities also warn that some Ayurvedic products have contained lead, mercury or arsenic.
With any herb, the cautions are the same. Most have not been studied in pregnancy, several can interact with hormonal medicines, blood thinners or other prescriptions, and none should be started without telling your doctor, particularly before surgery or fertility treatment. See how we approach this on our Chinese medicine and herbal medicine pages.
When to see a doctor
See your doctor or gynecologist if:
- Period pain keeps you from work, school or normal activities.
- Over-the-counter pain medicine does not help.
- Pain occurs at times other than just before or during your period.
- You have pain with sex, bowel movements or urination.
- You pass blood clots larger than a quarter, or bleed between periods.
- Period pain is new or clearly worse than it used to be.
- You have been trying to conceive without success.
Go to an emergency department for sudden severe pelvic pain, pain with fever or vomiting, pain with fainting, or pelvic pain with a positive pregnancy test.
Frequently asked questions
How do I know if my period pain is normal?
Pain that is manageable with a heating pad or an over-the-counter pain reliever and lasts a day or two is typical. Pain that disrupts your life, resists medication, or occurs outside your period should be assessed.
Can endometriosis be seen on an ultrasound?
Sometimes. Ultrasound and MRI can show ovarian cysts caused by endometriosis and some deeper disease, but small surface patches often do not show. A normal scan does not exclude it.
Does endometriosis always cause infertility?
No. Many women with endometriosis become pregnant. It does make conception harder for some, and it is common among women being evaluated for infertility.
Will acupuncture treat my endometriosis?
It does not treat the disease itself. One sham-controlled trial found less period pain during a 12-week course, with the benefit fading after treatment stopped. It can be used alongside medical care for pain, not in place of it.
Is it safe to take herbs with hormonal treatment?
Not automatically. Some herbs affect how medicines work or have hormone-like effects. Ask your doctor or pharmacist before combining them, and avoid herbal products in pregnancy unless your obstetric provider approves.
Does insurance cover acupuncture for period pain?
Coverage depends on your plan and often on the condition being treated. You can request a free benefits check before booking.
Netra Integrative Health Clinic provides acupuncture and herbal medicine as complementary care alongside your gynecologist's treatment. The clinic is at 5001 Hadley Road, Suite 210, South Plainfield, NJ 07080, open Monday to Saturday, 9:00 AM to 6:00 PM, by appointment only. Call (908) 402-7301 or schedule an appointment online.
This article is general information and does not replace an assessment by your own doctor. Severe or worsening period pain should be evaluated by a physician.