



















Planning a visit? See Ulcerative colitis care in South Plainfield for what care at our clinic involves.
An ulcerative colitis flare is a return of active inflammation in the colon, and it is treated with prescription medicine under a gastroenterologist. Complementary care has a smaller, supporting role. Curcumin taken alongside standard medicine has the most trial evidence. Diet helps general health but has not been shown to prevent flares reliably. Acupuncture and Ayurvedic treatment have been studied only in small or low-quality trials. None of these replaces the drugs that control the disease, and nothing in this article is a reason to stop or change them.
What ulcerative colitis is
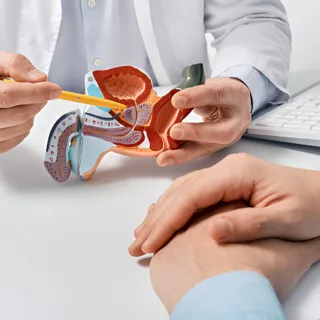
Ulcerative colitis (UC) is a chronic inflammatory bowel disease in which abnormal immune reactions cause inflammation and ulcers on the inner lining of the large intestine. The National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK) estimates that 600,000 to 900,000 people in the United States have it. It most often begins between ages 15 and 30, though it can start at any age. The cause is not fully known; genes, immune reactions, the gut microbiome and environmental factors all appear to contribute.
UC is not the same as irritable bowel syndrome. IBS does not inflame or damage the bowel lining. UC does, which is why it is monitored with blood tests, stool tests and colonoscopy.
Symptoms, and what a flare looks like
NIDDK lists the common symptoms as:
- Diarrhea
- Blood in the stool or rectal bleeding
- Abdominal cramping and pain
- Mucus or pus in the stool
- Tenesmus, a constant feeling of needing to pass stool even when the bowel is empty
- Urgency
More severe disease can bring fatigue, fever, nausea or vomiting, and weight loss. Doctors grade severity partly by stool frequency: fewer than four bowel movements a day is considered mild, more than six severe, and more than ten bloody bowel movements a day is fulminant disease that needs hospital treatment.
The disease runs in cycles. Periods of remission, when symptoms disappear, can last weeks or years. A flare, or relapse, is the return of symptoms. People often look for a trigger such as stress, an infection, a course of anti-inflammatory painkillers or missed doses of maintenance medicine, and sometimes there is no obvious reason at all. The aim of treatment is to reach remission and stay there.
Long-standing inflammation carries risks beyond the bowel symptoms: anemia, bone loss, blood clots and a raised risk of colorectal cancer. For that reason NIDDK describes surveillance colonoscopy every one to three years, typically starting eight years after symptoms began.
Standard treatment
The American College of Gastroenterology updated its UC guideline in 2025, and treatment is chosen according to how much of the colon is involved and how active the disease is. The main medicine groups described by NIDDK are:
- Aminosalicylates (such as mesalamine) for mild to moderate disease and for maintaining remission
- Corticosteroids for moderate to severe flares, for short periods only
- Immunosuppressants for moderate to severe disease
- Biologics for moderate to severe disease and for maintenance
- Small-molecule medicines for adults who do not respond to or cannot tolerate other options
Surgery to remove the colon is recommended for cancer or precancerous change, for life-threatening complications, and when medicines do not control symptoms or control them only with long-term steroids.
Two practical points from NIDDK are worth knowing during a flare. Acetaminophen is preferred for mild pain, because nonsteroidal anti-inflammatory drugs such as ibuprofen and naproxen can make symptoms worse. And you should ask your doctor before taking any dietary supplement.
If you think a flare is starting, contact your gastroenterology team early. Adjusting treatment in the first days is easier than rescuing a severe flare later.
Diet: useful, with limits
People with UC are offered more diet advice than almost any other group of patients, much of it contradictory. The research position is fairly modest. NIDDK states that studies have not found specific foods that cause UC or make it worse, and suggests a food diary to find personal triggers.
The American Gastroenterological Association's 2024 expert review on diet in inflammatory bowel disease advises that, unless there is a reason not to, patients follow a Mediterranean-style diet rich in a variety of fruits and vegetables, monounsaturated fats, complex carbohydrates and lean proteins, and low in ultraprocessed foods, added sugar and salt. It is candid about what diet cannot do: no diet has consistently been found to reduce the rate of flares in adults. The one specific note for UC is that a diet low in red and processed meat may reduce flares.
During an active flare many people temporarily tolerate softer, lower-residue foods better, such as cooked vegetables, soups, rice, bananas, eggs and fish, and then widen the diet again in remission. Long lists of forbidden foods carry their own risk. The AGA review stresses that malnutrition is under-recognised in inflammatory bowel disease and that a registered dietitian should be part of the care team.
Curcumin: the best-studied supplement
Curcumin is the yellow pigment in turmeric, a spice used in both Ayurvedic and Chinese medicine. It has been tested in UC as an addition to mesalamine-type medicine, never as a substitute.
A Cochrane review on curcumin for maintaining remission found only one eligible trial, with 89 patients who all continued sulfasalazine or mesalamine. Those given curcumin 2 grams a day for six months relapsed less often than those given placebo (4% versus 18%), a difference that did not reach statistical significance. At 12 months there was no significant difference.
More trials have appeared since. A 2025 meta-analysis of eight randomized trials with 482 patients found that adding curcumin to standard therapy increased the chance of clinical remission compared with placebo (relative risk 2.33) and improved endoscopic appearance, with no serious adverse events reported. The authors called the results promising while pointing to the small number of studies and the large variation between them, and asked for bigger trials.
So curcumin is a reasonable topic to raise with your gastroenterologist. It is not a proven treatment. Cautions apply:
- Products differ widely in curcumin content and absorption. The National Center for Complementary and Integrative Health (NCCIH) notes that liver injury has been reported with some highly bioavailable formulations. Stop and seek advice if you develop dark urine, yellowing of the skin or eyes, nausea or unusual fatigue.
- NCCIH states that turmeric supplements may be unsafe in pregnancy. Turmeric as a cooking spice is a different matter.
- Check with your doctor or pharmacist before starting, especially if you take blood thinners, diabetes medicine or immunosuppressants. Herbal products can interact with prescription drugs.
Acupuncture
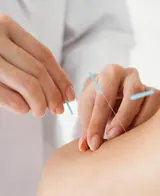
A 2020 systematic review of 13 randomized trials with 1,030 participants reported that acupuncture combined with mesalazine gave better symptom and colonoscopy results than mesalazine alone, with no difference in adverse events. The review authors warned that their findings must be interpreted with caution because the trials had a high or unclear risk of bias. Treatment in those studies lasted only 14 to 60 days, and the trials compared acupuncture with medicine, not with sham (placebo) acupuncture.
In plain terms, acupuncture has not been shown to control colitis. Where it may reasonably be used is for the things that travel with chronic bowel disease, such as abdominal discomfort, stress, poor sleep and low mood, while your medical treatment continues unchanged. According to NCCIH, reported complications of acupuncture have mainly involved nonsterile needles or improper technique. Tell your acupuncturist if you take immunosuppressants, biologics, steroids or blood thinners, since these affect infection and bruising risk.
Ayurveda and herbal medicine
Classical Ayurvedic texts describe conditions with bloody diarrhea under names such as raktatisara, understood as aggravated pitta affecting the colon. Traditional management includes a bland, cooling diet, buttermilk preparations, and herbs such as kutaja, bilva and turmeric. Panchakarma texts also describe medicated enemas.
The evidence is thin. In its overview of Ayurvedic medicine, NCCIH says few well-designed trials support Ayurvedic approaches in general, and the only digestive research it cites is the small turmeric studies in UC. Apart from curcumin, no Ayurvedic herb or procedure has reliable trial evidence in this disease.
Safety needs particular attention in UC:
- An inflamed colon is fragile. Purgation therapies and enemas given outside medical care are not appropriate during a flare, and should only be considered at all with your gastroenterologist's agreement.
- NCCIH reports that some Ayurvedic products have contained lead, mercury or arsenic. Use only products whose full contents are disclosed.
- Herbs can interact with immunosuppressants and other medicines, and many are not established as safe in pregnancy. Check with your doctor or pharmacist first.
The European Crohn's and Colitis Organisation estimates that up to half of people with inflammatory bowel disease use some form of complementary medicine at some point. Gastroenterologists expect the question. Tell yours what you are taking.
When to see a doctor
Call your gastroenterologist promptly if you notice more frequent or bloody stools, new urgency or night-time bowel movements, or symptoms returning after a period of remission. Seek urgent or emergency care for:
- Heavy rectal bleeding, or passing blood clots
- More than six bloody stools a day, especially with fever or a fast heartbeat
- Severe or rapidly worsening abdominal pain, or a swollen, tender abdomen
- Persistent vomiting or signs of dehydration, such as dizziness and very little urine
- A swollen, painful leg or sudden shortness of breath, which can signal a blood clot
- Fever while taking steroids, immunosuppressants or biologics
Complications such as perforation and toxic megacolon develop quickly and are life-threatening. A flare of this kind is treated in hospital.
Frequently asked questions
What does an ulcerative colitis flare feel like?
Typically diarrhea with blood or mucus, cramping, urgency and a feeling of incomplete emptying. Fatigue, fever and weight loss suggest a more severe flare.
Can diet stop a flare?
No diet has consistently been shown to prevent or stop flares in adults. A Mediterranean-style diet is recommended for general health, and eating less red and processed meat may reduce UC flares.
Should I take turmeric or curcumin for UC?
Trials suggest curcumin added to standard medicine may help some people reach or keep remission, but the studies are small and inconsistent. Discuss it with your gastroenterologist and pharmacist first, and do not use it in place of prescribed treatment.
Can acupuncture or Ayurveda put ulcerative colitis into remission?
There is no reliable evidence that either does. They may be used as supportive care for comfort and stress while medical treatment continues.
Is it safe to try complementary therapies during a flare?
See your gastroenterologist first. During a flare, avoid new herbal products, purgatives and enemas unless your specialist has approved them.
Netra Integrative Health Clinic offers acupuncture and Ayurvedic care strictly as an add-on to gastroenterology care. The clinic does not order labs, prescribe drugs or diagnose medical disease, and we ask patients with UC to stay under the care of their specialist. We are at 5001 Hadley Road, Suite 210, South Plainfield, NJ 07080, open Monday to Saturday, 9:00 AM to 6:00 PM, by appointment only. Call (908) 402-7301 or schedule an appointment. A first visit is a 60-minute consultation.
This article is general information and does not replace an assessment by your own doctor or gastroenterologist. Never stop, reduce or change prescribed medicine for ulcerative colitis without your specialist's advice.